Healthcare in Thailand is genuinely good, genuinely affordable by international standards, and genuinely confusing to arrive into. This is an attempt to lay out how it actually works for someone living here on a visa rather than visiting.
The three systems
Thailand runs a universal coverage scheme for Thai nationals, a social security scheme for people in formal employment, and a large private sector. As a foreign resident, the first is not available to you, the second may be if you are employed here, and the third is what most expats end up using.
Social security, if you are enrolled through an employer, ties you to one registered hospital and covers treatment there. It is real cover and worth understanding, but the hospital assignment and the standard of facilities are the reasons most expats supplement it rather than rely on it.
What private hospitals are like
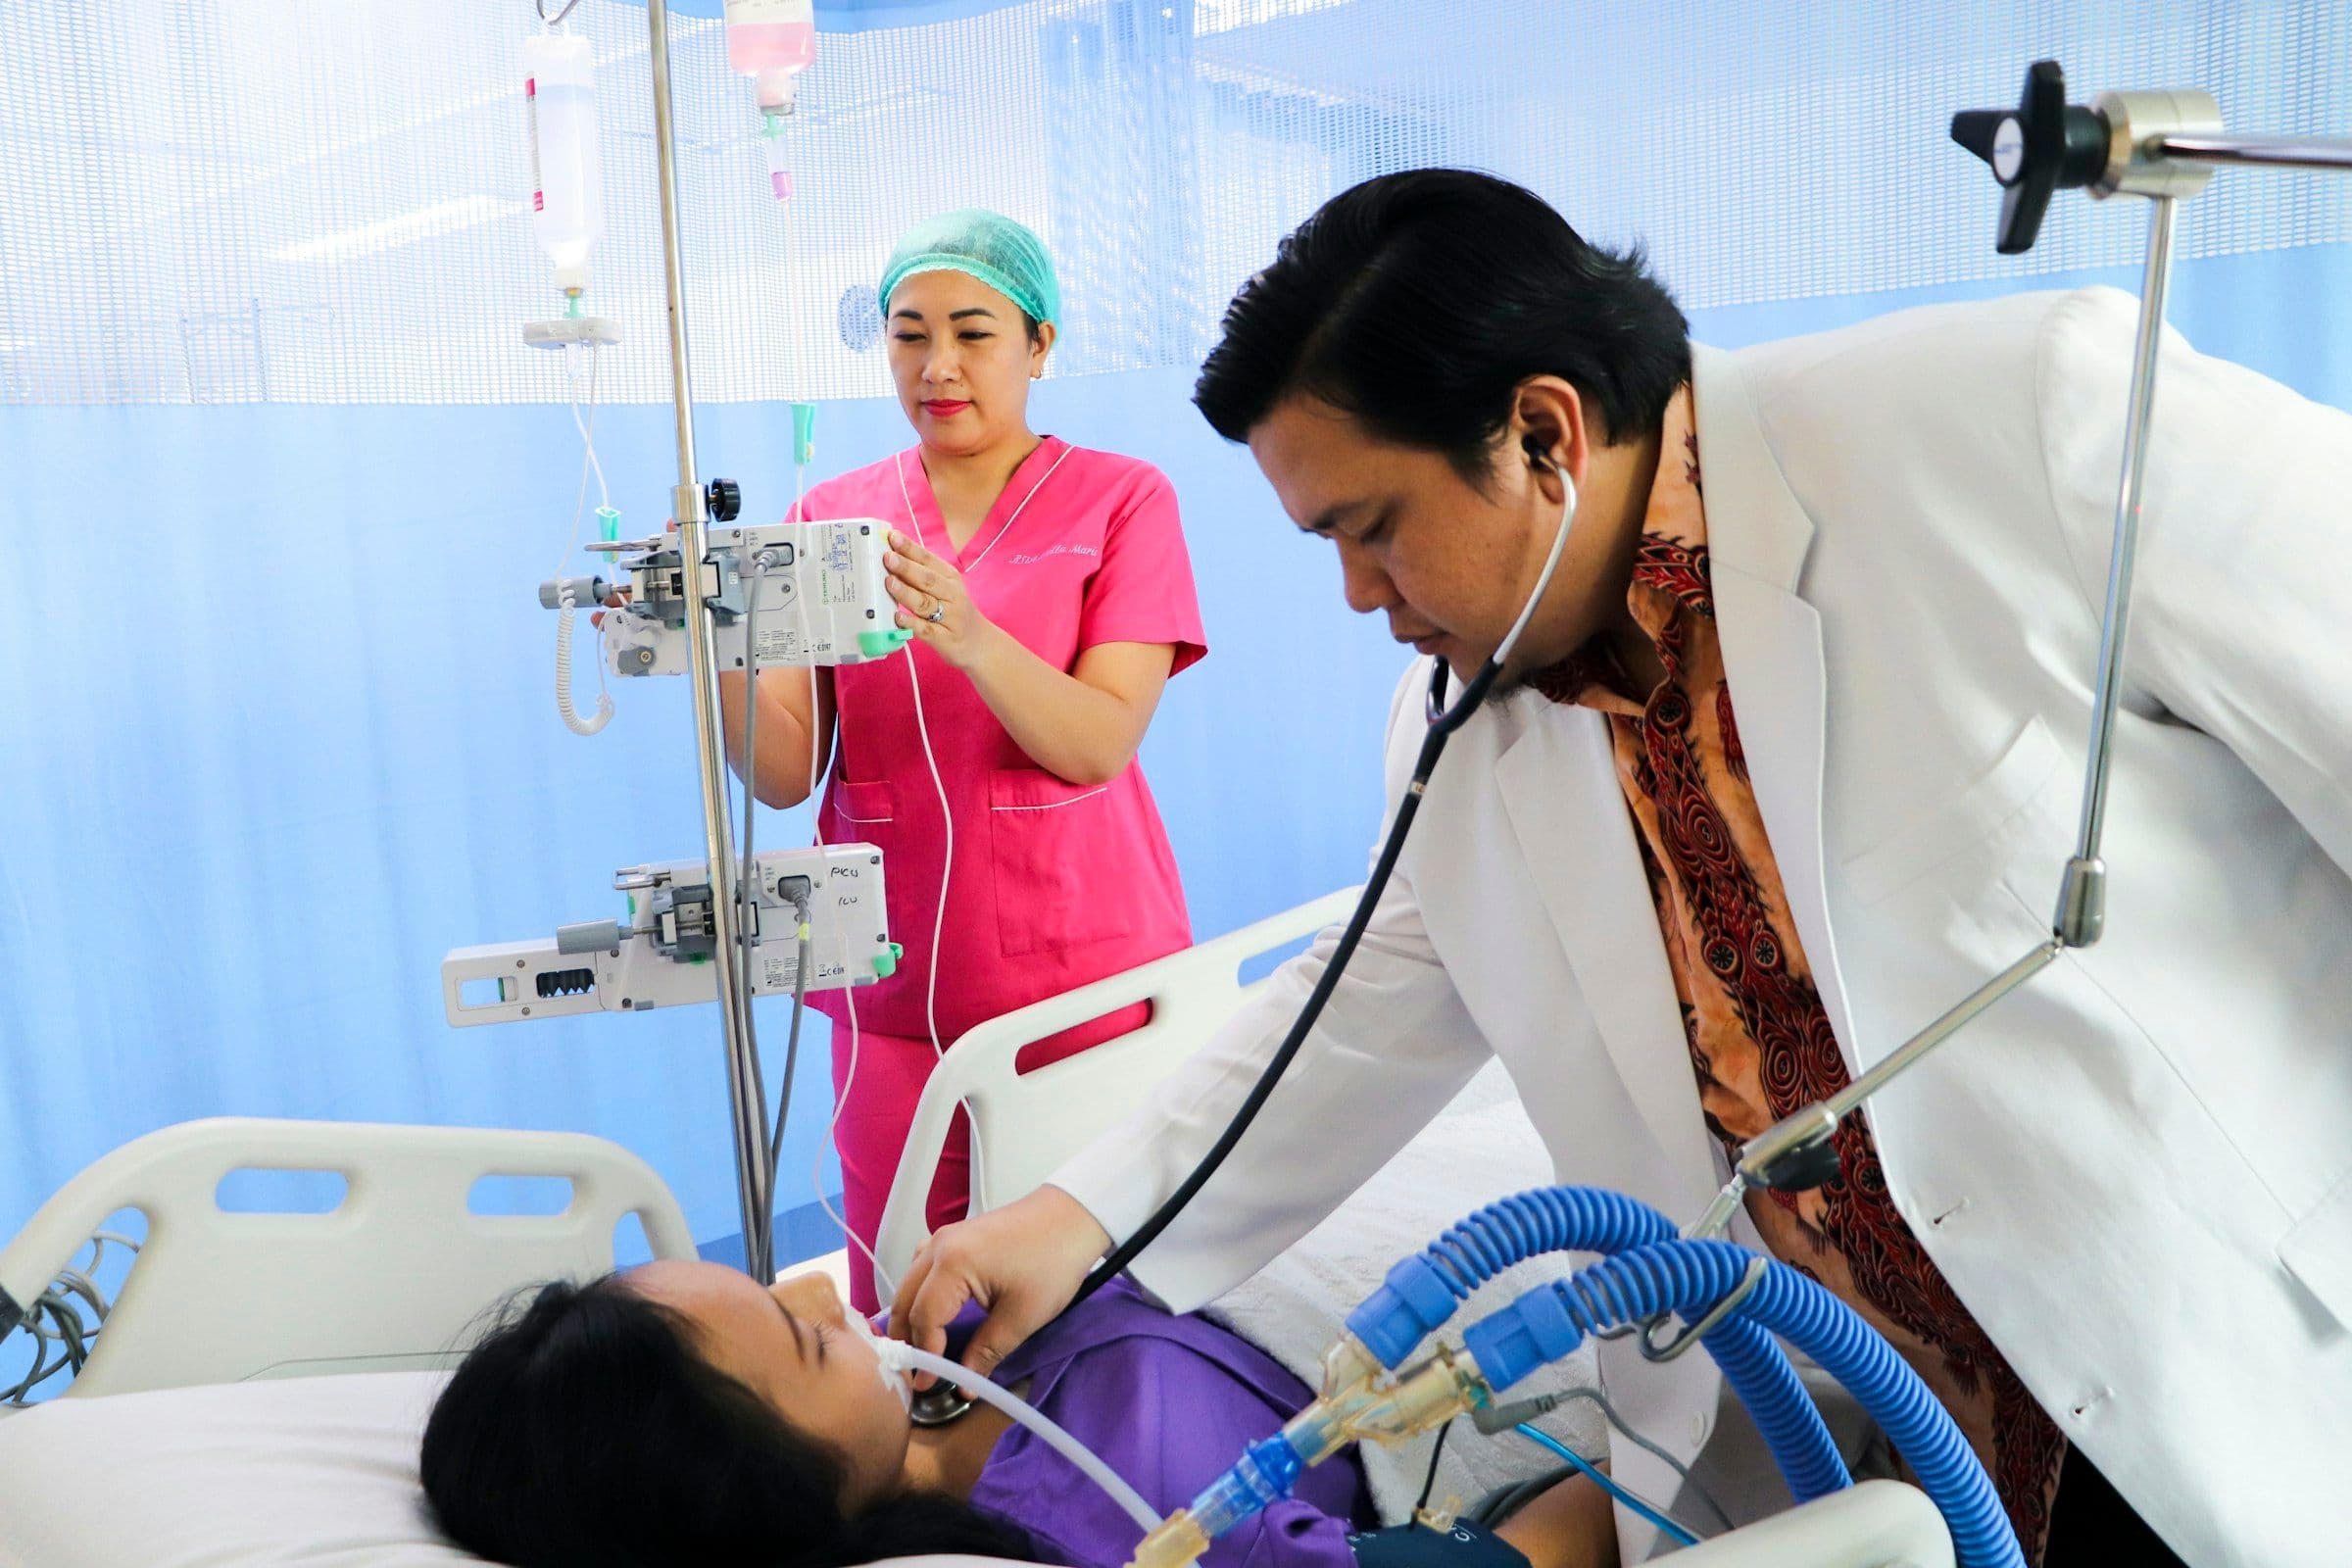
The major private hospitals in Bangkok, Chiang Mai and Phuket are comparable to good private care anywhere: short waits, English-speaking doctors, modern equipment, and a service culture closer to a hotel than a clinic.
They are also organised by specialty rather than general practice. You will often be seen by a specialist directly for something that would have started with a GP elsewhere, which is efficient but can mean paying specialist rates for minor problems.
Payment is expected at the point of service. There is no system that quietly bills you later, and no safety net that absorbs the cost if you cannot pay.
Where insurance fits
Private medical insurance in Thailand is written as a rider attached to a life policy — you cannot buy a standalone medical policy here. This surprises almost everyone, and it is a product regulation rather than a sales tactic.
The practical consequence is that your premium has two parts: a life policy, which usually accumulates a surrender value, and the health rider, which is pure annual risk cover.
Inpatient versus outpatient
Most policies are built around inpatient treatment — being admitted — because that is where the large, unpredictable costs are. Outpatient cover is often optional, and priced accordingly.
For most people this is the right shape. A consultation and some tests is an expense you can absorb; a week in hospital with surgery is a different order of magnitude, and that is what insurance is genuinely for.
The two things that decide what you pay
The first is the annual limit, which should be chosen by reference to the hospital you would actually use rather than to the premium you had in mind. Work out what a serious admission costs there, then pick a limit that covers it.
The second is whether you take a deductible. Agreeing to cover the first slice yourself reduces the premium substantially while leaving the top end — the part that protects you — intact. If you also have employer cover for smaller claims, this is often the best-value structure available.
Underwriting, and why timing matters more than anything
Your policy is priced and its exclusions set based on your health on the day you apply. Anything already diagnosed is generally excluded; anything that arises after the policy starts is covered, subject to the terms.
That single fact drives most sensible advice about health insurance here. Waiting until you feel you need it is precisely the wrong strategy, because by then the thing you need it for is on your record and excluded.
Waiting periods
No policy covers you fully from day one. There is an initial period during which illness is not covered, and longer waiting periods for specific conditions such as tumours, hernias and cataracts. Accidents are usually covered immediately.
This is normal and applies across insurers. It matters mainly when switching policies — leave the old one running until the new one’s waiting periods have passed if you can.
Disclosure
Declare your full medical history, including things you think are trivial. Non-disclosure is the leading cause of rejected claims, and it is almost never deliberate — people simply forget a course of medication or assume an old abnormal result did not matter.
An exclusion on one condition still leaves you with a working policy. An undisclosed condition can undermine the whole thing.
Where to start
Decide which hospital you would go to tonight in an emergency. Find out whether your insurer bills it directly. Choose a limit that covers a serious admission there. Declare everything. Then stop worrying about it.
If you would like someone to walk through this with you in English, our advisors will do it at no cost and without a pitch.